
Reproductive immunology
Reproductive immunology looks at whether the immune system, or a clotting or autoimmune problem, is contributing to repeated miscarriage or to failed implantation. At EVE Women and Fertility Clinic in Gunjur, Bangalore, Dr. Swati Shree uses guideline-supported tests, explains where the evidence is strong and where it is weak, and does not recommend treatments that have not been shown to work.
At a glance
- Who it may help
women with recurrent pregnancy loss (two or more), or repeated failed embryo transfers
- Strongest-evidence test
antiphospholipid antibodies, which cause antiphospholipid syndrome (APS)
- Proven treatment in APS
blood-thinning treatment during pregnancy, started and monitored by a doctor
- Often not recommended by guidelines
routine natural killer (NK) cell tests, and immune treatments such as IVIG or intralipids outside research
- At EVE
a clear explanation of which tests are useful in your situation, and which are not



What is reproductive immunology?
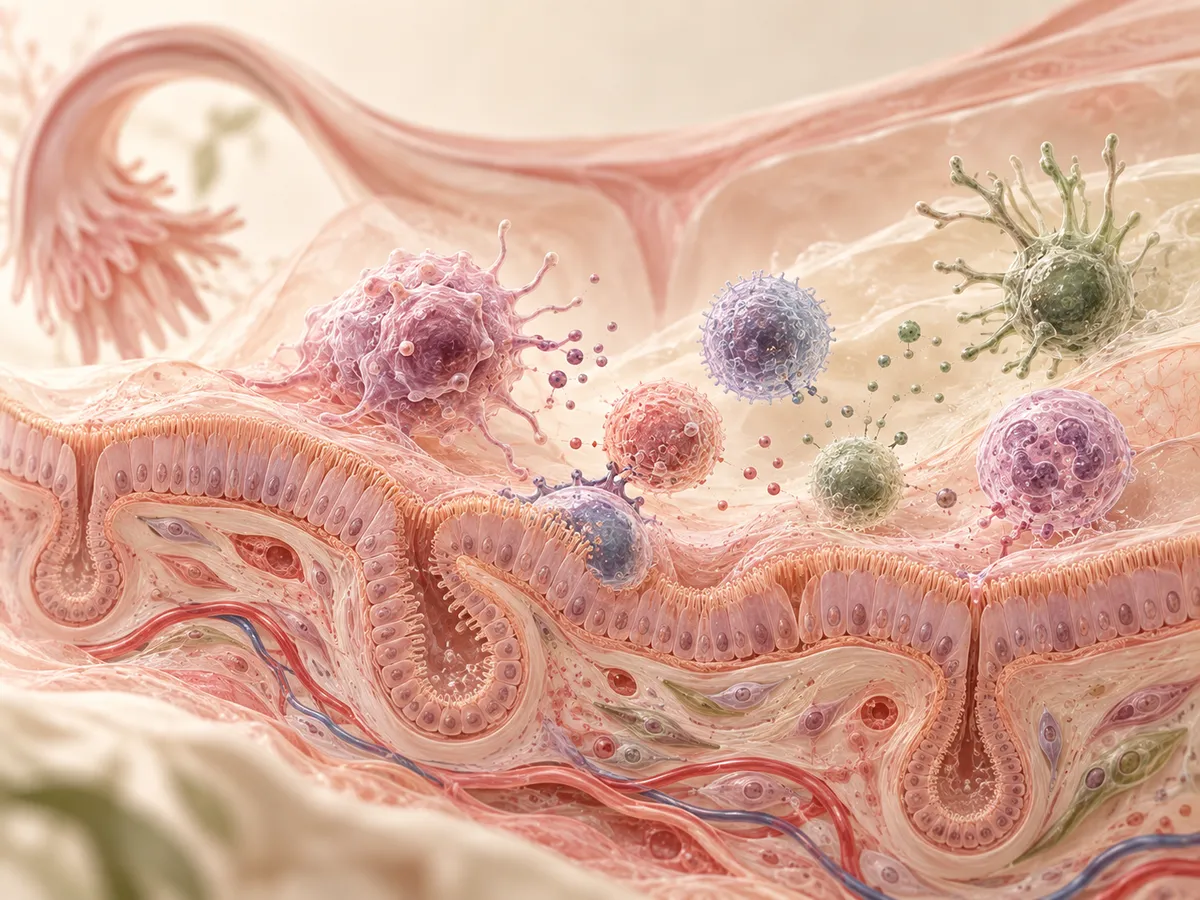
A pregnancy is half foreign to the mother's body, so the immune system must adapt. In a few women, an abnormal immune or clotting response may contribute to pregnancy loss. Reproductive immunology studies this area. It is a field with some well-proven findings and many contested claims. Being honest about both is the aim of this page.
What the evidence supports
- Antiphospholipid syndrome (APS): an autoimmune condition, found by blood tests on two occasions at least 12 weeks apart, that raises the risk of miscarriage and clots. Treatment with low-dose aspirin and heparin during pregnancy improves outcomes in confirmed APS.
- Thyroid autoimmunity: thyroid antibodies are linked to a higher risk of miscarriage in some studies. Thyroid function is checked and treated as needed. See Thyroid and fertility.
- Other autoimmune disease: such as lupus, when known, needs joint care with a rheumatologist.
What the evidence does not support
- Routine NK cell testing in blood or in the uterine lining does not reliably predict loss or guide treatment, according to ESHRE and RCOG guidance
- Routine testing for inherited thrombophilia in women with recurrent loss is not advised outside research or special situations
- Immune treatments such as IVIG, intralipid infusions, steroids or lymphocyte immunisation have not been shown to improve live birth rates in unexplained recurrent loss, and some carry risks
Where tests or treatments have limited evidence, Dr. Swati says so plainly. If you are considering them, she will explain what is known, what is not, and the cost and risk.
What happens at EVE
Review your history
of pregnancy losses, the weeks at which they happened, and any tests already done.
Basic tests first:
scans of the uterus, thyroid function, blood sugar, and other causes of recurrent loss. See Recurrent pregnancy loss.
Targeted immune tests
such as antiphospholipid antibodies, when your history fits.
Plan:
if APS is confirmed, a treatment plan with monitoring is made. If tests are normal, supportive care and early scans are planned.
Follow-up
in early pregnancy, with scans and clear communication.

Limits
Not every loss has an immune cause. In about half of couples with recurrent loss, no cause is found, and many of those go on to have a healthy pregnancy with supportive care. A test that is not recommended by guidelines is also not a reliable reason to buy a costly treatment.
FAQs
Is reproductive immunology proven?
Part of it is. Antiphospholipid syndrome is a well-established cause of recurrent miscarriage, with proven treatment. Other areas, such as NK cell testing and immune therapies, are not supported by current guidelines. Dr. Swati explains which category your situation falls into.
Should I have an NK cell test?
Guidelines from ESHRE and RCOG do not recommend routine NK cell testing in recurrent loss or failed IVF, because results do not reliably predict outcomes or guide treatment. If you are considering it, Dr. Swati explains the evidence and the cost first.
What is antiphospholipid syndrome?
APS is an autoimmune condition where antibodies raise the risk of blood clots and pregnancy loss. It is diagnosed by blood tests repeated at least 12 weeks apart. In pregnancy it is treated with blood-thinning medicine, which improves the chance of a healthy pregnancy. An immune condition where certain antibodies raise clotting risk and are linked to recurrent miscarriage. It is found on blood tests and treated in the next pregnancy with aspirin and heparin.
Can immune treatments like IVIG or intralipids help me?
Current guidelines do not recommend them for unexplained recurrent miscarriage or failed implantation, because trials have not shown that they improve live births. Some carry risks. Dr. Swati will not recommend an unproven treatment as routine.
Do I need a thrombophilia test?
Not routinely. ESHRE advises against testing for inherited thrombophilia in recurrent loss outside research or special cases, such as a personal or strong family history of clots. Dr. Swati decides after reviewing your history.
What if my tests are all normal?
Normal results are reassuring. Many women with unexplained recurrent loss go on to have a healthy pregnancy with early scans, supportive care and close follow-up. Dr. Swati continues to support you, and rechecks if something changes.
Sources
- ESHRE Guideline: Recurrent pregnancy loss (2022)
- RCOG Green-top Guideline No. 17: Recurrent first-trimester and second-trimester miscarriage
- ASRM Practice Committee, Evaluation and treatment of recurrent pregnancy loss (2012)


